


Stapled haemorrhoidopexy (PPH) treats Grade 3 and 4 internal haemorrhoids by lifting prolapsed tissue back into place with a circular stapler placed above the pain-sensitive dentate line. That usually means less pain and faster recovery than conventional haemorrhoidectomy. Stapled haemorrhoidopexy works well but only for the right presentation. Grade 1 and 2 piles, significant external haemorrhoids, and fibrotic tissue that can’t be repositioned are not suitable for this approach.
According to Dr. Rajeev Premnath, piles specialist in Bangalore, “Stapled haemorrhoidopexy gives excellent results in the right Grade 3 and 4 patient but offering it to someone with predominantly external disease or fibrotic piles is a setup for a poor outcome and a frustrated patient.”
Who Is a Good Candidate for Stapled Haemorrhoidopexy?
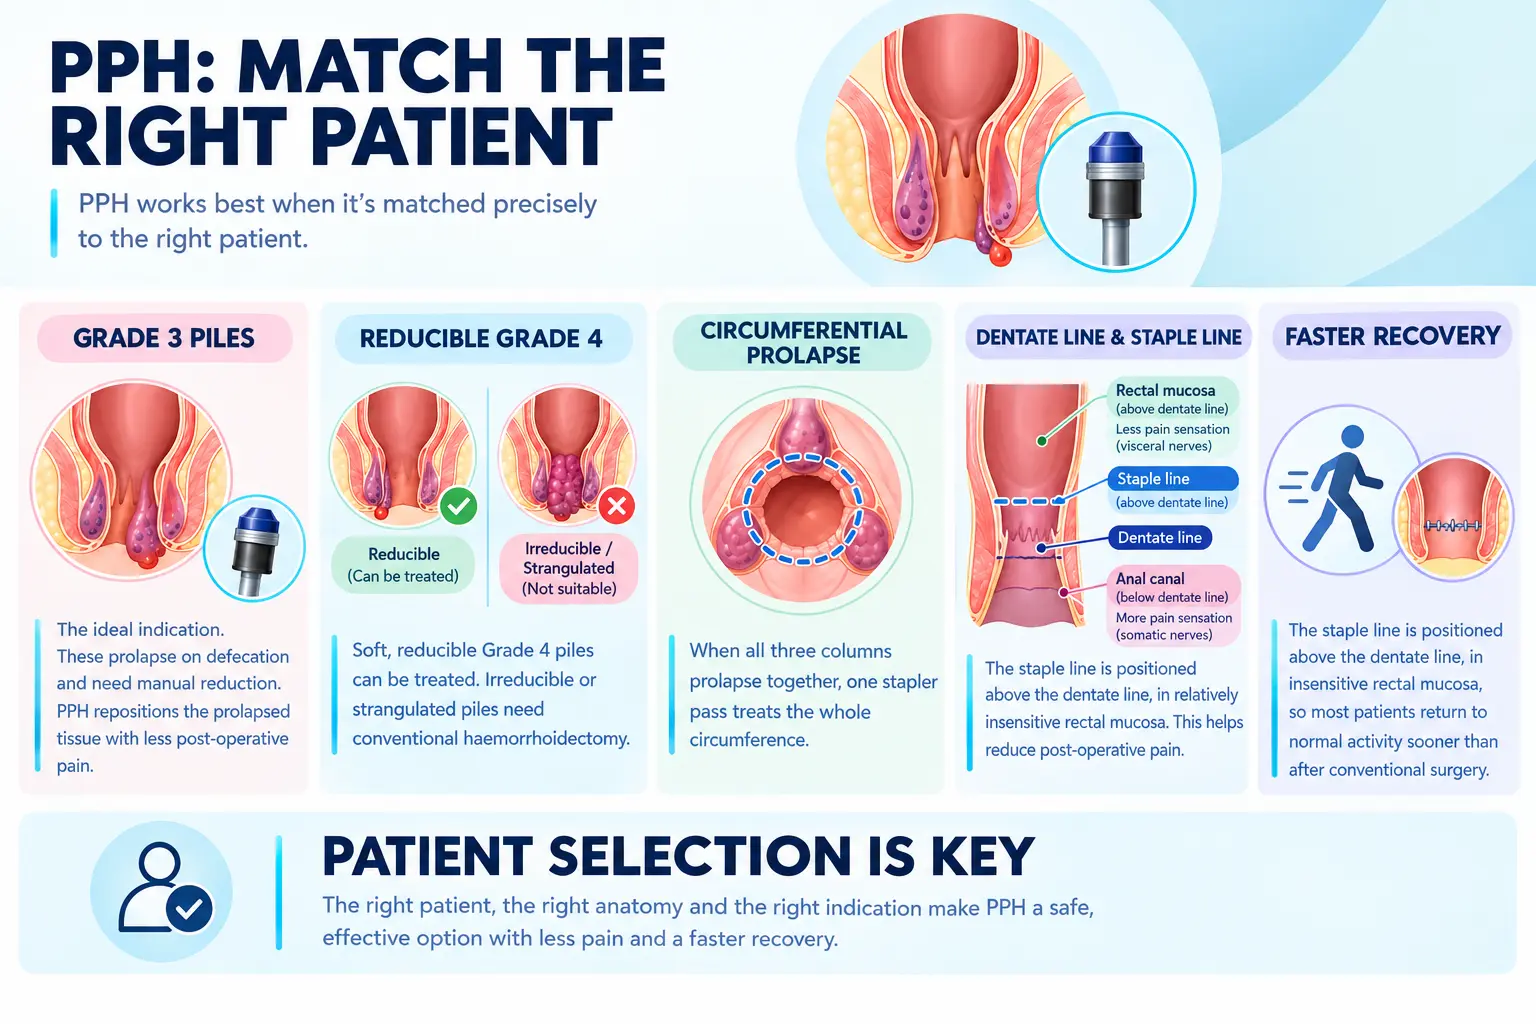
PPH only treats internal disease, so the right grade and anatomy decide the outcome, as explained in our piles treatment in Bangalore care.
Who Should Not Have Stapled Haemorrhoidopexy?
Ignoring the contraindications leads to recurrence, persistent symptoms and occasional serious complications.
- External Haemorrhoids: They sit below the dentate line, so the stapler doesn’t treat them. Significant external disease needs conventional surgery.
- Fibrotic or Irreducible Piles: The stapler can’t reposition tissue that won’t be pushed back, which risks poor staple placement and recurrence.
- Grade 1 and 2 Piles: These respond well to rubber band ligation or sclerotherapy. Surgery isn’t justified.
- Anal Stenosis or Prior Surgery: Distorted or narrowed anatomy raises the risk of bleeding and stenosis at the staple line.
Recurrence after PPH can be higher than after conventional haemorrhoidectomy, so choose the procedure by grade and anatomy, not recovery speed alone. Learn how to tell external from internal haemorrhoids before deciding.
Why Choose Dr. Rajeev Premnath?
Dr. Rajeev Premnath has over 20 years of experience as a General and Laparoscopic Surgeon, holding MS (Gen Surg.), FRCS (Glasg), FEBS, FICS, FACS, FIAGES and FMAS, with international training at IRCAD France and the National University of Health, Singapore. He heads the Day Care Surgery Department at Ramakrishna Specialty Hospital, Bangalore, and performs the full range of surgical piles treatments including stapled haemorrhoidopexy, laser haemorrhoidoplasty and conventional haemorrhoidectomy matched to each patient’s grade, anatomy and recovery needs.
Every piles patient presenting with prolapse is assessed on haemorrhoidal grade, degree of circumferential prolapse, external component size, and prior treatment history before stapling is recommended. A grade 3 with uniform circumferential prolapse and no significant external disease gets a different plan from a grade 4 with large skin tags and asymmetric columns and that distinction is what determines whether the procedure succeeds or the patient is back in clinic within 18 months.
Diagnosed with Grade 3 or 4 piles and wondering whether the stapler procedure is the right option for you?
FAQs
What grade of piles is stapled haemorrhoidopexy used for?
It’s indicated for Grade 3 and selected Grade 4 internal haemorrhoids with reducible prolapse.
Is stapled haemorrhoidopexy painful?
Post-operative pain is significantly less than conventional haemorrhoidectomy because the staple line is above the dentate line.
Can stapled haemorrhoidopexy treat external haemorrhoids?
No, PPH only addresses internal prolapsing haemorrhoids; external disease requires a different surgical approach.
What is the recurrence rate after stapled haemorrhoidopexy?
Recurrence rates are higher than conventional haemorrhoidectomy in some patients, which is why careful candidate selection matters.