


A giant inguinoscrotal hernia develops when an inguinal hernia enlarges over years until bowel, omentum, or bladder descends into the scrotum in large volumes. By the time patients present, operative complexity is completely different from standard hernia repair. Contents outside the abdominal cavity long enough create a physiological problem when returned not just a technical one.
According to Dr. Rajeev Premnath, a trusted General and Laparoscopic Surgeon in Bangalore, “This is not a bigger version of the same operation. Bowel that’s been in the scrotum for years has lost its place in the abdomen. Pushing everything back creates pressure the diaphragm can’t accommodate. Pneumoperitoneum conditioning, staged repair, nutritional optimisation these aren’t optional. They’re what separates a safe recovery from an ICU admission.”
Who Qualifies for Antibiotic Treatment of Appendicitis?
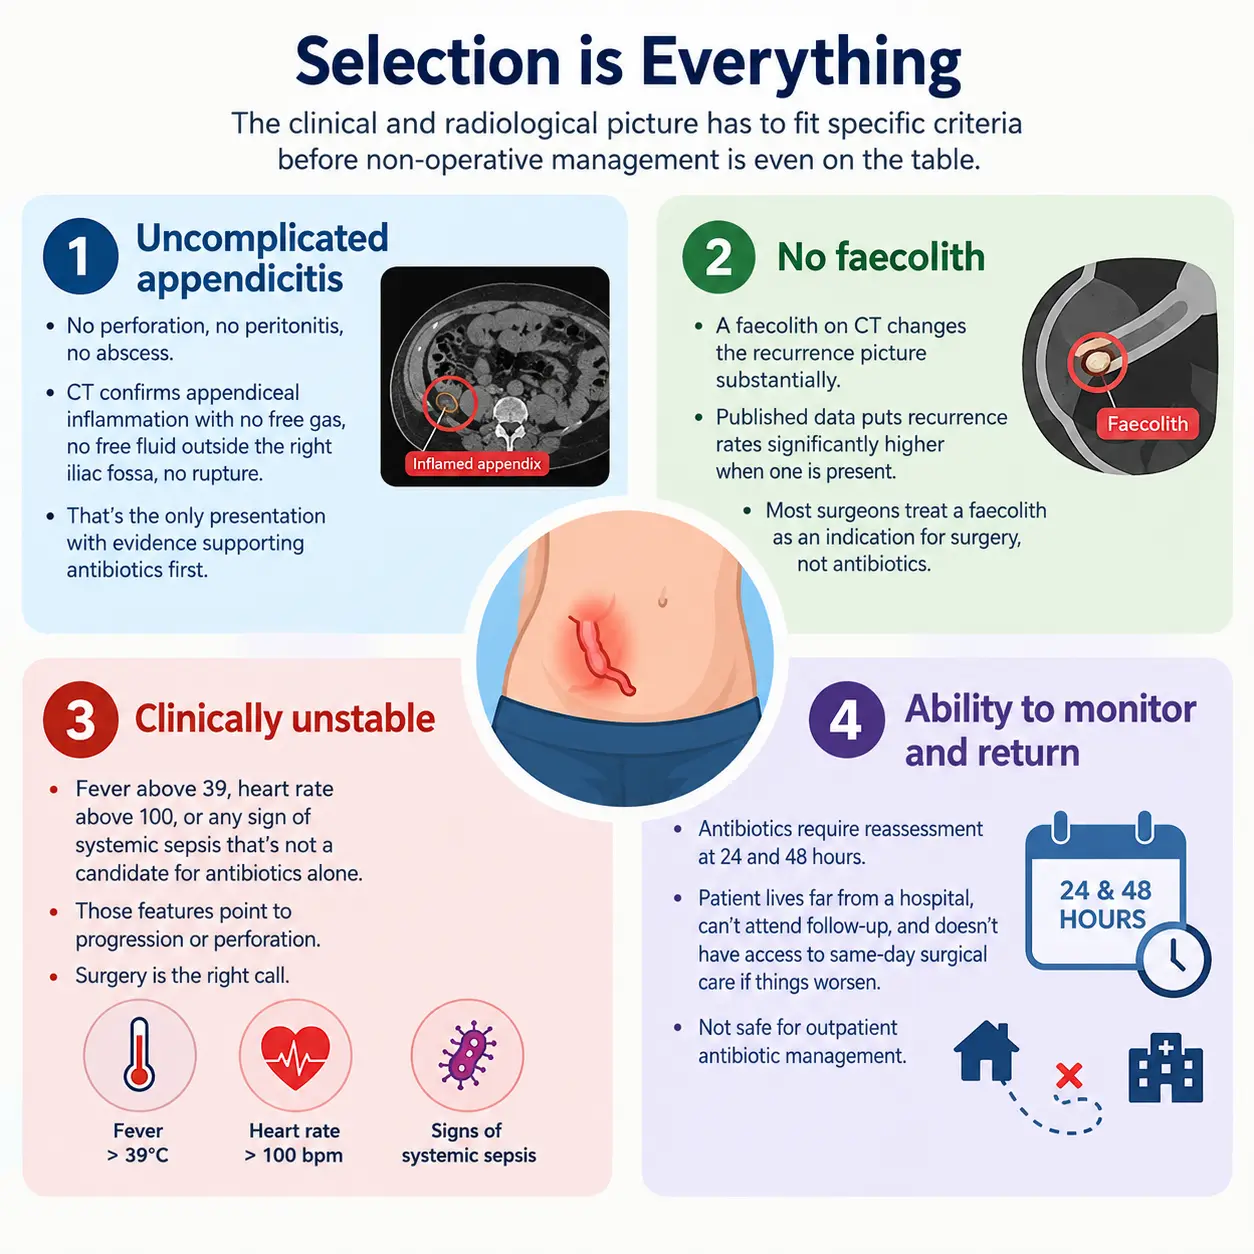
Not every case of appendicitis qualifies. Criteria eliminate a significant proportion. For a full overview of appendix treatment options, visit our appendix treatment page.
What Are the Outcomes and Risks of Choosing Antibiotics Over Surgery?
The evidence supports offering it. The evidence is also clear about the limits.
- Short-term success: 70% to 80% of patients with uncomplicated appendicitis on IV antibiotics avoid surgery during the index admission. Most turn the corner in 48 to 72 hours. Discharge once eating normally and inflammatory markers are dropping.
- Recurrence: 20% to 30% develop recurrent appendicitis within a year. Most recurrences in the first six months. Laparoscopic appendectomy manages them without higher complication rates than primary surgery, provided it isn’t an emergency.
- Risk of deterioration: A small proportion worsen despite antibiotics. Perforation. Abscess. Emergency surgery in less controlled conditions. That’s the real downside. Which is why 48-hour monitoring isn’t optional; it’s what catches the ones who are going the wrong way.
- Long-term picture: APPAC trial five-year data puts cumulative recurrence at around 40%. This isn’t a one-and-done decision for most patients. Some will need surgery eventually. Better to plan that proactively than arrive at it in an emergency.
Non-operative management is a genuine option, not a shortcut. Our blog on appendix surgery recovery covers what laparoscopic appendectomy involves when surgery becomes necessary.
What Happens During Antibiotic Treatment and How Is Progress Monitored?
Non-operative management isn’t discharge with a prescription. It’s a structured in-hospital protocol with defined review points.
- Initial admission: Admitted on IV antibiotics covering Gram-negative organisms and anaerobes. Oral intake restricted until pain and nausea settle. Inflammatory markers checked at baseline.
- 24 to 48-hour review: CRP, white cell count, and clinical examination repeated at both points. Improving continue. Pain worsening, fever persisting, abdomen more tender; surgery without delay.
- Conversion to oral antibiotics: Patients responding to IV treatment switch to oral at 48 to 72 hours. Discharged once tolerating food and clinically stable. Total antibiotic course: seven to ten days.
- Discharge and follow-up: Discharged with clear return instructions. Any return of pain, fever, or vomiting means same-day review, not waiting at home. Follow-up at four to six weeks confirms resolution and determines whether interval appendectomy is appropriate.
Monitoring is what separates safe non-operative management from a missed deterioration. For patients where surgery is the right answer from the start, visit our appendix treatment page.
Diagnosed with appendicitis and want to understand whether antibiotics are an option?
FAQs
Can appendicitis be treated with antibiotics instead of surgery?
Yes in selected cases. Uncomplicated appendicitis without perforation, faecolith, or peritonitis resolves with antibiotics in around 70% to 80% of patients short-term.
Who is not suitable for antibiotic treatment of appendicitis?
Patients with a faecolith, perforation, peritonitis, abscess, or systemic sepsis. None of these are candidates for non-operative management.
What is the recurrence rate after antibiotic treatment for appendicitis?
Around 20% to 30% within one year, rising to approximately 40% at five years. A real long-term risk patients need to understand before choosing antibiotics.
Is surgery still needed if antibiotics work initially?
Not immediately. But ongoing surveillance is needed and an interval appendectomy decision should be made proactively before recurrence forces an emergency.